What the Anion Gap Reflects
The anion gap value is a helpful way to assess serum electrolytes and suggest whether there are extra acids in the blood that are not directly measured on a routine chemistry panel. It is based on the principle of electrical neutrality: the body keeps the total positive and negative charges in balance, even though many charged particles are not individually reported on routine labs.
An anion gap calculator applies a few common values from serum chemistry to calculate this balance. The result can support clinical assessment of acid-base balance and help identify patterns such as metabolic acidosis. The calculation is not a diagnosis by itself, but it is a helpful diagnostic aid when paired with the rest of the lab picture and the patient’s symptoms.
Although sodium, chloride, and bicarbonate are the core values used in most calculations, the meaning of the result is broader. A changed anion gap can reflect an anion deficit, an increase in unmeasured anions, or shifts in the relationship between chloride and bicarbonate. That is why the number should always be interpreted as part of a complete acid-base review rather than in isolation.
How to Operate an Anion Gap Calculator
An anion gap calculator is simple to use, but accurate calculator inputs make a difference. Most versions ask for three values from the electrolyte panel: sodium, chloride, and bicarbonate. Some calculators also allow optional potassium input, depending on the formula being used.
To work with the tool well:
- Input the most recent lab results from the same sample when possible. Enter the bicarbonate or total CO2 value reported by the lab as instructed. Verify the units match the calculator format, usually milliequivalents per liter. Review whether potassium is included in the formula before interpreting the number.
The calculator is most useful when paired with a quick look at the broader clinical picture. For example, a low bicarbonate level with a rising anion gap suggests a different pattern than a low bicarbonate level with a normal anion gap. That distinction can inform next-step testing and help narrow the differential diagnosis.
Because the result depends on the lab values you enter, even small input errors can affect the interpretation. Recheck sodium, chloride, and bicarbonate before relying on the output for lab interpretation.
Anion Gap Formula and Calculation Steps
The standard anion gap formula is expressed as:
Na minus Cl minus HCO3
Here, sodium is the primary measured cation, while chloride and bicarbonate are the recorded anions. The calculated gap represents unmeasured charged particles not routinely measured on standard serum electrolytes. Some clinicians include potassium, but many commonly used formulas do not.
Stepwise calculation:
- Start with the sodium value. Take away chloride. Subtract bicarbonate, also written as HCO3. The resulting value is the anion gap, reported in milliequivalents per liter.
For example: if sodium is 140, chloride is 102, and bicarbonate is 24, the calculation is 140 - 102 - 24 = 14 milliequivalents per liter. That result may fall within a expected reference range depending on the lab method used.
These lab values must be interpreted carefully because different analyzers, reagents, and reporting conventions can shift the expected range. The formula itself is simple, but the clinical meaning depends on context, trending, and whether the patient has an acid-base disorder.
Normal Anion Gap Interval and Interpretation
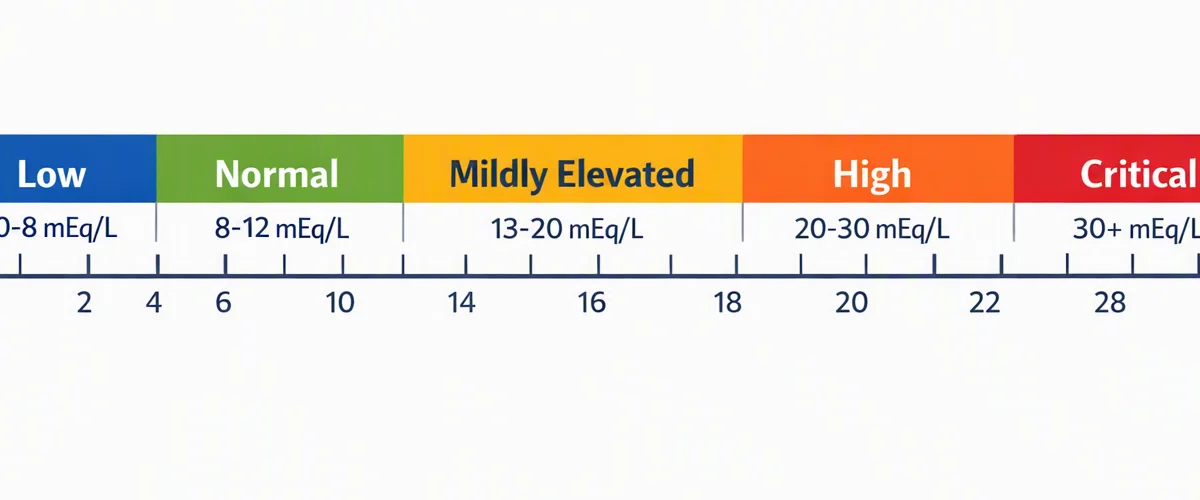
The expected anion gap can be not identical across all laboratories. The precise lab range depends on the testing method, whether potassium is accounted for, and how the lab measures bicarbonate. Many clinicians think of a common non-potassium range as roughly 8 to 12 milliequivalents per liter, but the local lab range should always be used first.
Interpretation gets more nuanced when albumin is abnormal. Albumin is a major unmeasured anion, so low albumin can decrease the apparent gap and hide an underlying problem. In that setting, a corrected anion gap may offer a more accurate reflection of the true acid burden.
Albumin correction matters because the raw number may not fully reflect the severity of systemic acidosis when albumin is reduced. A patient with hypoalbuminemia can have a deceptively normal result even when high anion acids are present. That is why albumin correction is an essential part of lab interpretation.
Practical interpretation often follows this pattern:
- Normal gap: consider bicarbonate loss with chloride retention. Elevated anion gap: consider added acids or unmeasured anions. Decreased gap: consider albumin, lab variation, or less common causes.
Reduced, Typical, and Elevated Anion Gap Acidosis
Metabolic acidosis is a major reason clinicians evaluate the anion gap. The number serves to classify whether the bicarbonate drop is being matched by a rise in chloride or by the accumulation of unmeasured acids. This distinction differentiates high anion gap acidosis from non-anion gap acidosis.
In high anion gap acidosis, the body has accumulated acids that deplete bicarbonate without a corresponding increase in chloride. Common examples include lactic acid buildup and ketoacid production. In non-anion gap acidosis, bicarbonate falls but chloride rises to maintain electrical neutrality, creating a normal gap pattern.
A normal gap does not mean acid-base status is normal. It simply means the pattern is consistent with bicarbonate loss balanced by chloride gain. That is why the anion gap is a pattern interpretation tool, not a stand-alone verdict.
Renal failure is an important cause of high gap changes because impaired kidney function can reduce acid excretion and allow acids to accumulate. At the same time, some kidney-related acid-base disorders may produce a normal gap pattern, especially when tubular dysfunction or bicarbonate wasting is involved.
Low values are less common but still important. A low result may reflect hypoalbuminemia, a laboratory artifact, or unusual cation excess. Clinical correlation is necessary before drawing conclusions.
How Blood Bicarbonate Matters
Blood bicarbonate is key to the calculation because it makes up part of the formula and because it shows the body’s ability to buffer. The term bicarbonate in this context usually means the reported serum bicarbonate or total CO2, which is commonly used as a proxy for HCO3.
Changes in bicarbonate influence the anion gap in a direct way. If bicarbonate falls and chloride does not rise enough to offset it, the gap rises. If bicarbonate falls while chloride rises, the gap can remain normal. That is why bicarbonate input is essential for reliable calculator output.
Bicarbonate also helps determine whether the body is compensating for an acid-base disturbance. A low bicarbonate level may represent a primary metabolic problem, Look at this website or it may reflect metabolic compensation for a respiratory disorder. Thoughtful review helps separate these possibilities.
In practical terms, bicarbonate is one of the most informative values in acid-base disorders because it provides a quick view of buffering status. It helps connect the anion gap calculation to the patient’s overall acid-base balance rather than treating the number as an isolated calculation.
Typical Causes of an Abnormal Anion Gap
An abnormal gap often indicates a handful of major causes. Some of the most significant causes involve increased acid production or impaired acid clearance. These include lactic acidosis, ketoacidosis, and conditions associated with kidney disease.
Lactic acidosis can occur when tissues are underperfused, oxygen-deprived, or otherwise stressed, causing lactate to rise and bicarbonate to fall. Ketoacidosis is often seen in uncontrolled diabetes, prolonged starvation, or alcohol-related states, where ketone acids lead to a high gap.
Kidney disease can increase retained acids and limit the body’s ability to regenerate bicarbonate. This may produce a high gap, a normal gap, or mixed findings depending on the severity of dysfunction and the specific acid-base disorder involved.
Toxins are an additional important consideration. Certain ingestions can create a high anion gap by introducing unmeasured acids or interfering with metabolism. In these cases, the calculation can act as a clue that triggers urgent investigation.
Common categories to consider include:
NAGMA causes- Accumulation of lactate Ketone accumulation Retention of acids by the kidneys Toxic ingestion Mixed acid-base disorders involving bicarbonate and chloride
The pattern of serum electrolytes, the clinical story, and any associated symptoms should inform the next step in evaluation.
When to Evaluate the Need for Further Testing
An unusual finding often justifies additional testing, especially when the clinical picture suggests a significant acid-base disorder. An arterial blood gas can help determine pH, respiratory status, and whether there is a mixed disorder. A venous blood gas may also be useful in many situations when arterial sampling is not necessary.
An electrolyte panel is often the first step, but additional labs can help clarify the cause of the abnormal gap. Repeating serum chemistry may be useful if there is concern about specimen error, changing status, or a rapidly evolving electrolyte imbalance.
An albumin level should be considered when the gap seems unexpectedly normal or low. Because albumin contributes to the unmeasured anion pool, hypoalbuminemia can mask a clinically meaningful elevation. In that case, a corrected value can better reflect the underlying acid burden.
Further testing is especially reasonable when there are signs of worsening illness, kidney dysfunction, toxin exposure, severe dehydration, or unexplained systemic acidosis. The anion gap is a useful screening measure, but it is only one piece of a broader diagnostic aid.
FAQs About the Anion Gap Calculator
What does an anion gap calculator used for?
An anion gap calculator is used to measure the gap between measured cations and anions from basic lab data. It helps with lab interpretation, especially when evaluating metabolic acidosis, acid-base disorder patterns, and possible causes of electrolyte imbalance.
Why does the calculator need blood bicarbonate input?
Blood bicarbonate is part of the formula and a key marker of acid-base balance. Without bicarbonate input, the calculator cannot accurately calculate the anion gap or show whether a drop in bicarbonate is associated with a high anion pattern, a normal gap pattern, or another acid-base shift.
How is a normal anion gap value?
A normal anion gap depends on the lab’s reference range and method. Many labs consider a value around 8 to 12 milliequivalents per liter typical when potassium is not included, but local reporting standards should always guide interpretation.
How to interpret a high anion gap result?
A raised anion gap indicates the presence of extra anions and typically points toward metabolic acidosis. Common causes include lactic acidosis, ketoacidosis, renal failure, and toxin ingestion. The result should be assessed with bicarbonate, pH data, symptoms, and the rest of the serum electrolytes.
Should you account for albumin when interpreting the anion gap?
Absolutely. Albumin is a important unmeasured anion, so low albumin can make the gap look falsely normal or low. A corrected anion gap can enhance interpretation and more clearly reflect the true acid-base balance, especially when the clinical picture suggests a hidden disturbance.
Medical disclaimer: This article is for educational purposes only and is not a substitute for professional medical advice, diagnosis, or treatment. An abnormal lab result should be reviewed by a qualified clinician in the context of the full clinical assessment.