An anion gap calculator is a practical diagnostic tool made to assist interpret a blood chemistry panel or electrolyte panel. It brings together serum sodium, chloride, and bicarbonate to produce a calculated value that aids clinical interpretation of acid-base balance. While the number itself is straightforward, the meaning behind it depends on the overall lab result, including albumin, the complete electrolytes, and the patient’s assessment.
This guide outlines how the anion gap works, how the anion gap formula uses sodium and related measurements, and why the result can point toward a certain metabolic disturbance such as metabolic acidosis or high anion gap metabolic acidosis. It also covers albumin correction, corrected anion gap use, reference range interpretation, and critical diagnostic limitations.
How this Anion Gap Shows
The anion gap measures the discrepancy between observed positive and negative charges in the blood. In plain language, it helps identify whether there are additional unmeasured ions in the body that may affect the body’s acid-base balance. Because the body keeps electrolytes in a narrow range, even small shifts in serum sodium, chloride, and bicarbonate can provide useful indications.
Most clinicians apply the anion gap as part of a broader serum chemistry review. It is not a standalone test. Instead, it is one piece of evidence that can guide the interpretation of a metabolic acidosis workup, especially when a patient has signs or other abnormal lab findings.
The idea behind the anion gap is that sodium is usually the main measured positive ion, while chloride and bicarbonate are two of the main measured negative ions. The gap reflects what is not directly measured. That is why the result can be useful when looking for hidden causes of a metabolic disturbance.
Anion Gap Formula
The standard anion gap formula is simple:
Anion gap = sodium - (chloride + bicarbonate)
Some tools may also include potassium, but many https://anion-gap-lookup099.novacrestiq.com/posts/anion-gap-calculator-for-acid-base-disorder-analysis modern references exclude it for clarity. The key inputs are the sodium concentration, chloride level, and bicarbonate level. After the values are entered into an anion gap calculator, the tool delivers a rapid measurement that can be compared with the usual reference range.
As an example, if the sodium is 140, the chloride is 102, and the bicarbonate is 24, the calculation is:
140 - (102 + 24) = 14
That calculated value may fall within many commonly used normal limits, depending on the lab. Because ranges vary, the result should always be interpreted alongside the specific laboratory’s reported range and the overall clinical interpretation.
Practically, the anion gap calculator is valuable because it streamlines the interpretation of a routine blood chemistry panel. The calculator does not replace judgment; it organizes the data so patterns become easier to spot.
How Serum Sodium Influences the Formula
Serum sodium is fundamental to the calculation because it anchors the formula. Since sodium is the most abundant measured cation in the blood, any change in its concentration can change the anion gap result. That does not mean sodium directly triggers the acid-base problem, but it can shape the final number and how the electrolyte balance is understood.
If sodium is low or high, the relationship between sodium, chloride, and bicarbonate shifts. The resulting lab result may still be informative, but the context matters. For example, a low sodium value can make the calculated gap less straightforward to interpret if the rest of the electrolytes are altered at the same time.
Albumin also matters here. Because albumin is a negatively charged protein, lower albumin can make the anion gap appear lower than it truly is. This is why albumin correction is sometimes used to estimate a corrected anion gap. In a patient with hypoalbuminemia, the unadjusted number may miss the degree of underlying acid-base abnormality.
The corrected result is not a separate diagnosis. Rather, it is a correction factor added to improve interpretation. This is especially important when the goal is to assess a hidden cause of metabolic acidosis or to detect a subtle change in serum chemistry.
Standard, Increased, and Reduced Anion Gap Results
The normal range for the anion gap depends on the testing method and whether potassium is included. That said, the result is usually categorized as normal anion gap, high anion gap, or decreased anion gap.
A normal anion gap often suggests that the measured electrolytes are well balanced in a usual way, though it does not automatically mean there is no problem. A elevated anion gap metabolic acidosis usually points to the presence of extra acids or unmeasured charged particles in the blood. A reduced anion gap is less common and may reflect low albumin, lab variation, or other issues that affect the measurement.
It is important to remember that “normal” is lab-specific. A result that seems borderline in one setting may be acceptable in another. This is why a full clinical review should consider the specific blood chemistry panel, the patient’s symptoms, and the broader acid base balance.
In practical terms:
- Anion gap within normal limits: may be seen when the electrolyte pattern does not suggest excess unmeasured acids. High anion gap metabolic acidosis: suggests extra acid accumulation or another process increasing the gap. Reduced anion gap: may indicate hypoalbuminemia, lab variation, or a less common abnormality.
Common Causes of Abnormal Anion Gap Values
A number of conditions can affect the anion gap and suggest a specific cause of metabolic acidosis. Among the most common are lactic acidosis, ketoacidosis, renal failure, and hypoalbuminemia.
Lactic acidosis occurs when lactate builds up faster than the body can clear it. This may be seen with low oxygen delivery, severe illness, or other metabolic stress. Because lactate is an unmeasured anion, the gap may rise.
Ketoacidosis can develop when ketones accumulate, such as in uncontrolled diabetes or prolonged fasting. These ketones raise the level of unmeasured acids, often leading to high anion gap metabolic acidosis.
Renal failure can reduce the body’s ability to eliminate acids. As acid retention increases, the anion gap may become elevated. This result may be especially informative when paired with the rest of the electrolytes and kidney-related markers on the blood chemistry panel.
Hypoalbuminemia, on the other hand, may lower the measured gap. Because albumin contributes to the negative charge balance, low albumin can make the result appear deceptively normal or reduced. This is where albumin correction and the corrected anion gap become useful in clinical interpretation.
Additional causes may also occur, but these four are among the most often evaluated when reviewing an elevated or reduced anion gap.
Stepwise: Understanding Calculator Output
Working through an anion gap calculator output is not just entering numbers and reading a result. A systematic process strengthens assessment and helps avoid mistakes.
Step 1: Review the electrolyte values. Inspect the serum sodium, chloride, and bicarbonate values from the electrolyte panel or blood chemistry panel. Verify the units and sample are correct.
Step 2: Calculate the anion gap. Use the anion gap formula to obtain the calculated value. Evaluate it with the lab’s reference range rather than relying on a universal cutoff.
Step 3: Consider albumin. If albumin is low, apply albumin correction to estimate the corrected anion gap. This may reveal a hidden elevation that would otherwise be missed.
Step 4: Match the pattern to the clinical picture. Identify signs of acid-base disorder, dehydration, kidney dysfunction, or other causes of metabolic disturbance. The result should align with the patient’s symptoms and other lab findings.
Step 5: Form a clinical interpretation. A single number is not enough. Integrate the anion gap with the rest of the serum chemistry, the history, and the physical findings to reach a reasonable conclusion.
NAGMA causesA useful anion gap result is one that supports the full story, not one that stands alone.
Constraints of Anion Gap Calculation
Although the anion gap is important, it has clear diagnostic limitations. The calculation depends on testing methods, lab handling, and the setting in which the result is used.
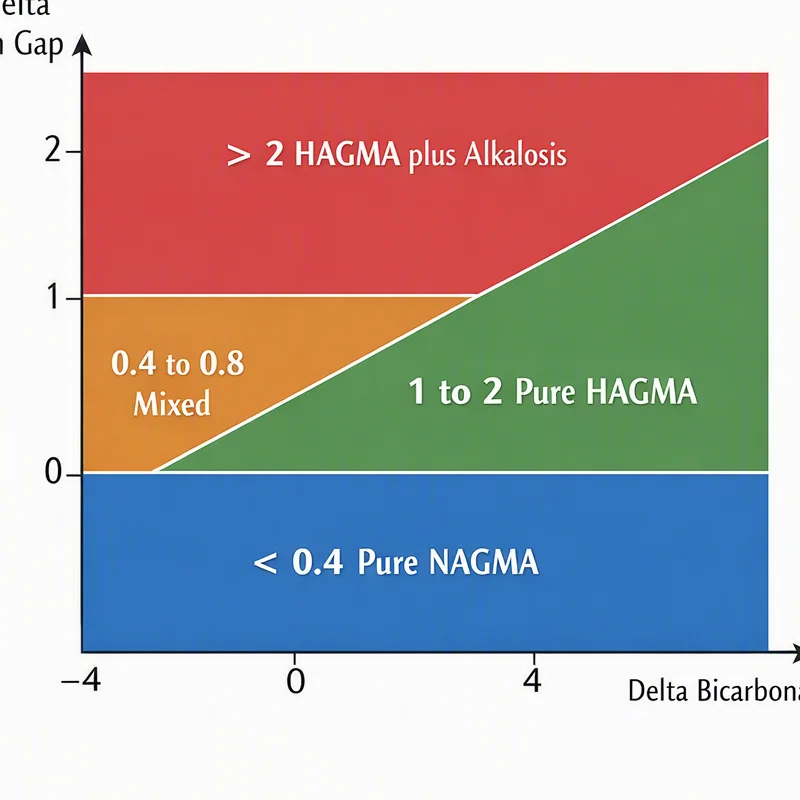
One limitation is albumin correction. When albumin is not considered, the result may mislead the reader. This is especially relevant in patients with hypoalbuminemia, where the measured gap can be artificially low or normal.
Another limitation is laboratory variation. Different analyzers and reporting methods can produce slightly different reference intervals. A number that seems abnormal in one lab may land in a different lab’s expected range.
The calculation also does not directly identify the cause of the problem. It simply points to the possible presence of unmeasured ions or a shifted electrolyte pattern. Additional testing and context are needed to confirm the cause, whether that is lactate acidosis, ketone-related acidosis, kidney failure, or something else.
Finally, the anion gap should not be used as a substitute for direct clinical care. It is best viewed as one part of a broader diagnostic approach to acid-base balance and clinical interpretation.
When to Seek Medical Review
Abnormal anion gap findings should be reviewed by a clinician, especially when they occur with concerning symptoms. Signs such as severe weakness, rapid breathing, confusion, vomiting, chest discomfort, or worsening illness may signal a serious acidotic state or another urgent condition.
An elevated or reduced result does not always mean emergency care is needed, but it does mean the test should be understood in context. If a blood test panel shows a concerning pattern, prompt prompt evaluation may be appropriate to assess the underlying cause.
Patients with diabetes, kidney disease, infection, dehydration, or known electrolyte imbalances may need a closer look if the anion gap is outside the normal range. The same is true if the result shifts notably from prior testing or does not match the patient’s clinical status.
When in doubt, check in with a clinician who can interpret the result alongside symptoms, exam findings, and other laboratory data.
FAQs About Anion Gap and Serum Sodium
What is an anion gap calculator with serum sodium used for?
An anion gap calculator with serum sodium is used to derive the anion gap from common electrolytes on a blood chemistry panel. It supports clinical assessment of acid-base problems, especially when evaluating metabolic acidosis or checking for a hidden metabolic issue.
How do you calculate the anion gap from sodium, chloride, and bicarbonate?
Use the anion gap equation: sodium - (chloride + bicarbonate). The sodium level, chloride concentration, and bicarbonate value are entered into the calculator to produce the final value.
Why does serum sodium matter in an anion gap calculation?
Serum sodium matters because it is the main measured cation in the formula. Changes in sodium can affect the final number and the way the acid-base status is interpreted. Sodium also helps anchor the relationship between the measured electrolytes and the overall charge balance.
What does a high anion gap mean?
A high anion gap often suggests extra acids or unmeasured ions in the blood. Common causes include lactic acidosis, ketoacidosis, and renal insufficiency. It can be a clue to high anion gap metabolic acidosis, but the full clinical picture is needed for interpretation.
Could a normal anion gap also point to a health problem?
Absolutely. A normal anion gap does not eliminate disease or an pH balance problem. Some cases may not change the gap much, and lab result review must factor in symptoms, other labs, and the patient’s overall condition. Medical interpretation should always extend past the number alone.